Dysphagia and Caregiver Burden: How to Look After Yourself Too


Seven years into managing my mother’s Level 3 diet, I calculated roughly how many modified meals I had prepared. Three meals a day, 365 days a year, for seven years. That’s somewhere over seven and a half thousand meals — each one tested, each one verified, each one carried to the table with the awareness that getting it wrong had clinical consequences.
I don’t say this to complain. I chose this. I would choose it again. But I say it because nobody, in all the clinical appointments and discharge letters and SLP consultations, ever asked how I was doing. The focus was always — correctly — on my mother. The person preparing her food three times a day was assumed to be managing.
The research says otherwise. Caregivers of family members with dysphagia are significantly more likely to report having little time for themselves and feeling depressed, lonely, and that caregiving was too much to handle. And the clinical consequence of that burden is significant: managing dysphagia independently contributes to caregiver burden, potentially increasing burnout and nonadherence to clinical recommendations.
That second finding is the one that stopped me when I first read it. Caregiver burnout doesn’t just harm the caregiver. It directly affects the safety of the person being cared for. A caregiver who is exhausted, isolated, and overwhelmed is more likely to skip the consistency test, more likely to take shortcuts with texture modification, more likely to miss the early signs that something has changed. Looking after yourself is not a luxury in dysphagia care. It is a clinical requirement.
This article is for every caregiver who has been handed a discharge letter, a thickener sample, and a list of IDDSI levels — and then been left to figure out the rest alone.
What Dysphagia Caregiving Actually Involves
Most discussions of caregiver burden in older adult care focus on the general challenges — helping with personal care, managing medications, navigating the healthcare system. Dysphagia caregiving involves all of these, and adds a layer that is uniquely relentless.
Food is not optional. Mealtimes happen three times a day, every day, without exception. Each meal requires preparation — blending, sieving, testing, portioning, reheating, retesting. Each drink requires preparation — measuring, mixing, waiting for the thickener to hydrate, testing the consistency. Each mealtime requires active supervision — monitoring for coughing, watching pace, prompting posture, responding to refusal.
There is no mealtime off. There is no day when texture modification doesn’t apply. There is no week where the rules temporarily relax because everyone needs a break. Other aspects of caregiving have natural rhythms of more and less demand. Dysphagia doesn’t.
Family caregivers experience statistically significant pressure and lack of required social and healthcare support. Caregivers providing substantial healthcare-related help for older adults are significantly more likely to experience emotional, physical, and financial difficulties, and to experience work productivity loss and reduced participation in valued activities.
The specific shape of dysphagia burden looks like this:
Time. The preparation time for a Level 3 or Level 4 meal is significantly longer than for a standard meal. Blending, sieving, and testing adds time to every cooking session. Batch cooking reduces this — but still requires a dedicated block of time two or three times per week that most caregivers do not have neatly free.
Mental load. The cognitive burden of dysphagia management is constant. Which level has been prescribed. Whether the consistency was right this morning. Whether she coughed more than usual yesterday. Whether the thickener is running low. Whether the upcoming family gathering can be navigated safely. This mental load doesn’t stop between mealtimes.
Social restriction. Eating is social. Dysphagia changes the social landscape of food — family mealtimes look different, eating out requires significant advance planning, spontaneous meals become complicated or impossible. Caregivers reported experiencing reduced dining outside, frustrated by difficulty finding appropriate food for patients. The isolation this creates affects both the person with dysphagia and the caregiver.
Emotional weight. There is a specific grief in watching someone lose the ability to eat normally. Food carries memory, culture, pleasure, and connection — all of it changed by dysphagia. Preparing a liquidised version of the meal everyone else is eating, watching the person manage three teaspoons before fatigue sets in, knowing this will progress — this is a particular kind of loss that is rarely named or acknowledged in clinical settings.
Why Caregiver Burden Matters Clinically — Not Just Personally
This is the finding I return to most often when I need to remind myself that looking after my own wellbeing is not selfish.
Managing dysphagia independently contributes to caregiver burden, potentially increasing burnout and nonadherence to clinical recommendations.
Nonadherence to clinical recommendations. That phrase matters. When a caregiver is exhausted and overwhelmed, the consistency test gets skipped. The chin tuck reminder stops happening. The oral hygiene routine after meals gets abbreviated. The weekly weighing stops. The signs of change go unnoticed.
The safety of dysphagia management at home depends on the caregiver being capable of implementing it consistently. A burnt-out caregiver cannot implement anything consistently. Supporting caregiver wellbeing is therefore not separate from clinical management — it is part of it.
Caregivers of spouses with dysphagia were significantly more likely to experience emotional burden, with an odds ratio of 2.06. Of those spouses caring for partners with dysphagia who reported emotional burden, nearly 70% rated the burden moderate to severe.
These are not unusual caregivers struggling with an unusual situation. Nearly 70% of spousal caregivers of people with dysphagia report moderate to severe emotional burden. This is the norm. And it is rarely directly addressed.
The Mealtime Burden Specifically
Of all the tasks in dysphagia caregiving, mealtime management is the one most consistently associated with elevated burden. Caregivers have to spend more time on food preparation or intake, and patients unable to eat naturally also cause a stressful dining atmosphere in the family.
The stress comes from multiple directions at once:
The safety anxiety. Every mealtime carries the awareness that an aspiration event is possible. This vigilance — watching every swallow, listening for the wet voice quality, monitoring the coughing — is exhausting to sustain across three meals a day. It creates a background level of alertness that doesn’t fully switch off even between mealtimes.
The refusal problem. When someone refuses thickened drinks or modified food — for entirely understandable reasons — the caregiver is caught between respecting the person’s autonomy and knowing the clinical risk of thin liquids or inappropriate textures. This is not a solvable dilemma. It is a tension that has to be managed, repeatedly, meal after meal. Our thickened drink refusal guide covers the practical strategies — but the emotional cost of navigating refusal is real and accumulates.
The isolation of knowledge. Most people around the caregiver — family members, friends, restaurant staff — have no understanding of what dysphagia management involves. Explaining why you can’t just order from the regular menu, why the soup can’t just be served straight from the pot, why you need to bring your own thickener to a family gathering — repeatedly, to people who don’t quite understand — is its own kind of exhaustion.
The nutrition worry. On top of everything else, most caregivers are managing a background anxiety about whether enough protein and calories are being consumed. The malnutrition risk in dysphagia is real, and the weekly weighing that should catch early problems is often the first thing to be dropped when time is short.
What Actually Helps — Practical Strategies That Reduce Burden
Coping strategies for caregivers can be mainly divided into problem-focused and emotion-focused approaches — acquiring knowledge related to dysphagia, seeking support, relieving the discomfort of patients, and distracting attention.
Both matter. The problem-focused strategies reduce the objective burden. The emotion-focused strategies help manage the subjective experience of it. Neither alone is sufficient.
Batch Cooking — The Single Most Effective Time Reduction Strategy
The most practical intervention available for reducing mealtime burden is batch cooking — preparing larger quantities two or three times per week rather than cooking every meal from scratch.
A single two-hour batch cooking session can produce:
- Five or six portions of blended chicken or fish in sauce — refrigerate for 48 hours, freeze beyond that
- Three or four portions of smooth soup — freeze in individual servings
- A week’s worth of porridge base — refrigerate and reheat by portion with added milk
Label everything with the IDDSI level and the date. Keep labelled portion containers in the freezer so any family member or professional carer can reheat a meal correctly without needing instruction.
This doesn’t eliminate the mealtime burden. But it changes the daily texture of it from urgent daily cooking to planned preparation sessions with clear endpoints — which is psychologically very different.
Our blenders guide and Level 4 diet guide cover the practical cooking techniques. The principle here is that systems reduce burden more than effort does.
Sharing the Load — What Other Family Members Can Learn
One of the most consistent findings in dysphagia caregiver research is that burden falls disproportionately on one person — almost always female, often a spouse or adult daughter. Other family members are frequently willing to help but don’t know enough about dysphagia management to do so safely.
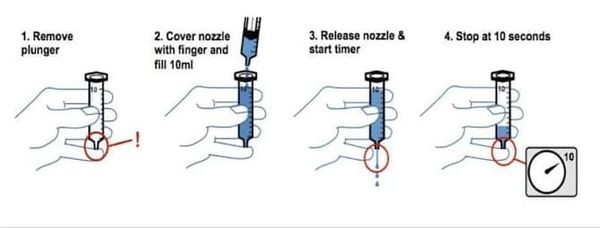
The solution is training, not delegation. A family member who hasn’t been trained to prepare Level 4 food correctly is not a safe substitute caregiver — they are a risk. But a family member who has spent two hours learning the spoon tilt test, the thickener mixing process, and the mealtime positioning protocol is a genuine source of relief.
What other family members need to know:
- The prescribed IDDSI level for food and liquid — written and posted in the kitchen
- How to prepare thickened drinks and verify the level
- How to reheat batch-cooked food and verify the consistency after reheating
- The basic mealtime protocol — positioning, pace, portion size
- What signs warrant a call to the primary caregiver
Printed on a single page and kept on the kitchen noticeboard, this is enough for a family member to manage a mealtime safely. Print the relevant IDDSI level handout from our printable resources page and keep it alongside the written protocol.
Professional and Community Support — What Exists and How to Access It
Adult day services use is associated with reduced caregiver stress, improved mood, and physiological stress reduction. On adult day services days, caregivers report lower negative affect and higher positive affect.
This finding is consistent and significant — structured respite is measurably beneficial. Not just helpful — measurably reducing stress biomarkers in caregivers who use it regularly.
Adult day programmes. Many adult day programmes have staff trained in modified texture diets and dysphagia management. Placing a family member with dysphagia in a day programme one or two days per week provides supervised mealtime support and gives the primary caregiver a genuine break from mealtime responsibility. This is worth investigating specifically — ask whether the programme has IDDSI-trained staff and whether they can manage the prescribed level.
Respite care. Short-term respite — a few days to a week with a trained carer or in a residential setting — provides the kind of extended rest that hour-by-hour breaks cannot. It requires planning and a comprehensive handover of the dysphagia management protocol, but the investment is worth it.
Community nursing. In many areas, community nurses can provide support with aspects of dysphagia management — particularly oral hygiene and monitoring. Ask the GP whether community nursing input is available.
Caregiver support groups. Focused dysphagia education could reduce caregiver stress and enhance overall well-being. Groups specifically for dysphagia caregivers are rare, but general dementia caregiver groups, stroke caregiver groups, and Parkinson’s caregiver groups often include members managing dysphagia. The specific experience of mealtimes is understood in these groups in a way it rarely is elsewhere.
The Emotional Reality — Naming What Most Clinical Guides Don’t
The grief of dysphagia caregiving is real and deserves to be named.
There is grief in the diagnosis — watching a person who ate normally, who cooked, who sat at a family table with everyone else, now require a liquidised version of every meal. There is ongoing grief each time the IDDSI level drops — from Level 5 to Level 4, from Level 4 to Level 3 — because each step represents function that has been lost.
There is the grief of family mealtimes that no longer work the same way. The birthday dinner where everyone eats normally and one bowl on the table looks different. The Christmas meal where you’ve spent hours preparing a Level 3 version of the food everyone else is eating, and you watch it barely touched.
There is the anticipatory grief of knowing, in progressive conditions, that this will worsen. Planning for what Level 3 will mean when it progresses to something harder still.
None of this is weakness. All of it is a rational response to genuine loss. The research confirms that of spousal caregivers of people with dysphagia who reported emotional burden, nearly 70% rated the burden moderate to severe. This is not an unusual experience. It is the common experience, unacknowledged.
What helps — in my experience and in the research — is having somewhere to put it. A caregiver support group, a therapist who understands chronic illness caregiving, a close friend who will listen without trying to fix it, a community of people who genuinely understand what you’re managing. Not solutions. Acknowledgement.
The Warning Signs of Caregiver Burnout
Burnout doesn’t arrive suddenly. It builds gradually, through accumulated fatigue and unmet needs, until the caregiver’s capacity to sustain safe care is genuinely compromised. These are the signs worth watching for in yourself:
Increasing resentment toward mealtimes or the person being cared for. Not the normal frustration of a hard day — a persistent, cumulative resentment that mealtimes feel like an obligation rather than a care act.
Skipping safety checks. Not testing the consistency. Not doing oral hygiene after meals. Not monitoring for coughing. When the safety protocols start being abbreviated consistently, this is a warning sign that capacity is running low.
Physical symptoms. Persistent fatigue that sleep doesn’t fix, headaches, digestive problems, increased illness. The physical toll of chronic stress is real and measurable.
Social withdrawal. Declining invitations, losing contact with friends, spending less and less time on anything outside the caregiving role.
Feeling that you cannot continue. The clearest signal. If you are regularly thinking that you cannot sustain this — take that seriously, not as a failure but as clinical information. The person you are caring for needs you to be functional. That requires addressing this.
Protecting Your Own Nutrition and Health
This section is short because it should not need to be long — but it does need to be said.
Caregivers in studies of chronic illness consistently show poorer nutrition, less physical activity, higher rates of depression, and more frequent illness than age-matched non-caregivers. The focus on the care recipient’s nutritional needs is clinically appropriate. The total neglect of the caregiver’s own needs is not.
Eat properly. This is easier to say than to do when time is short, and the focus is elsewhere. Batch cooking for the person with dysphagia creates a natural opportunity to cook for yourself at the same time. A caregiver who is skipping meals or eating whatever is fastest is not sustainable.
Sleep. If mealtime preparation and care responsibilities are disrupting sleep — address this directly. Sleep deprivation compounds every other aspect of burden.
Move. Any physical activity — walking, swimming, whatever is accessible — directly reduces stress and improves mood. The research is unambiguous. Even 20 minutes makes a measurable difference.
See your GP. Caregivers frequently defer their own medical appointments. Don’t. Your physical health is not separate from your capacity to care for someone else.
A Note on Asking for Help
Many caregivers resist asking for help — from family members, from professional services, from their GP. The reasons are familiar: not wanting to burden others, not trusting anyone else to do it correctly, feeling that asking for help is a form of failure.
None of these things are true. Asking for help is what sustains safe care over months and years rather than weeks. The family member who takes one mealtime a week is not replacing you — they are making it possible for you to continue.
Strategies such as information sharing, printed care plans, and educational resources can assist in the process of supporting care at different levels, especially after hospitalisation. The written protocol on the kitchen noticeboard, the labelled batch-cooked portions in the freezer, the printed IDDSI handout — these are the tools that make it possible for other people to help safely.
Let them help.
Resources for Dysphagia Caregivers
In the US:
- National Foundation of Swallowing Disorders — swallowingdisorderfoundation.com
- Caregiver Action Network — caregiveraction.org
- AARP Caregiver Resource Centre — aarp.org/caregiving
In the UK:
- Carers UK — carersuk.org
- RCSLT (Royal College of Speech and Language Therapists) — patient resources — rcslt.org
Condition-specific caregiver organisations:
- Alzheimer’s Association (US) — alz.org
- Stroke Association (UK) / American Stroke Association (US)
- MND Association (UK) / ALS Association (US)
Frequently Asked Questions
Is caregiver burden in dysphagia different from general caregiver burden?
Yes — managing dysphagia independently contributes to caregiver burden as a distinct factor, over and above general caregiving burden. The three-times-daily, non-negotiable nature of mealtime management creates a specific, relentless burden that is different in character from other caregiving tasks.
How do I know if I am experiencing caregiver burnout?
Key signs include persistent fatigue that sleep doesn’t fix, increasing resentment toward mealtimes, skipping safety protocols, social withdrawal, and a persistent sense that you cannot continue. These are not signs of weakness — they are signals that your capacity is being exceeded and intervention is needed.
What is the most practical thing I can do to reduce mealtime burden?
Batch cooking is the single most effective practical intervention — preparing multiple portions two or three times per week rather than cooking every meal from scratch. Combined with labelled portion containers and a written protocol for other family members, it reduces daily preparation time significantly and makes it possible for others to help safely.
Can I ask the GP for support with caregiver burden?
Yes — and you should. GPs can refer to carer support services, community nursing, social services for respite care, and mental health support. Mention specifically that you are managing dysphagia care three times daily — the concrete nature of the task helps the GP understand the level of burden rather than treating it as general caregiving stress.
What if no one else can learn to manage the dysphagia correctly?
Other family members can be trained. The core protocol — IDDSI level, thickener preparation, spoon tilt test, mealtime positioning — is learnable in two hours. Write it down. Demonstrate it. Let them practise with you present. A family member who has been properly shown the protocol is a genuine source of relief. Printed IDDSI handouts from our resources page help make the level visible and consistent across everyone involved.
References
Shune, S. & Namasivayam-MacDonald, A. (2025). Dysphagia symptoms contribute to greater care partner burden in neurodegenerative disease. American Journal of Speech-Language Pathology, 34(4), 2053–2061. https://doi.org/10.1044/2025_AJSLP-24-00529
Namasivayam-MacDonald, A. & Shune, S. (2024). Dysphagia management contributes to burden in caregivers of persons with dementia. Innovation in Aging, 8(Suppl 1). https://doi.org/10.1093/geroni/igae098.1627
Namasivayam-MacDonald, A. (2024). Characteristics of burden associated with caring for older family members with dysphagia across time. Innovation in Aging, 8(Suppl 1). https://pmc.ncbi.nlm.nih.gov/articles/PMC11688855/
Namasivayam-MacDonald, A. & Shune, S. (2018). Swallowing impairments increase emotional burden in spousal caregivers of older adults. Dysphagia, 34(2). https://pubmed.ncbi.nlm.nih.gov/30623709
Fong, E., et al. (2024). The perceptions and experiences of caregivers of patients with dysphagia: A qualitative meta-synthesis. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC11366769/
Li, Y. (2025). Respite care in adult day services: An updated systematic review from 2015 to 2025. Innovation in Aging. https://doi.org/10.1093/geroni/igaf122.851
Carneiro, D., et al. (2024). Home caregiver strategies for feeding older adults with dysphagia after dehospitalization. Revista da Escola de Enfermagem da USP. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11135044/
American Speech-Language-Hearing Association. (n.d.). Adult dysphagia (Practice Portal). https://www.asha.org/practice-portal/clinical-topics/adult-dysphagia/